Turn on cookies to sign in
Signing in saves your progress to your Curie account. We can only do that with cookies on — turn them on to continue.
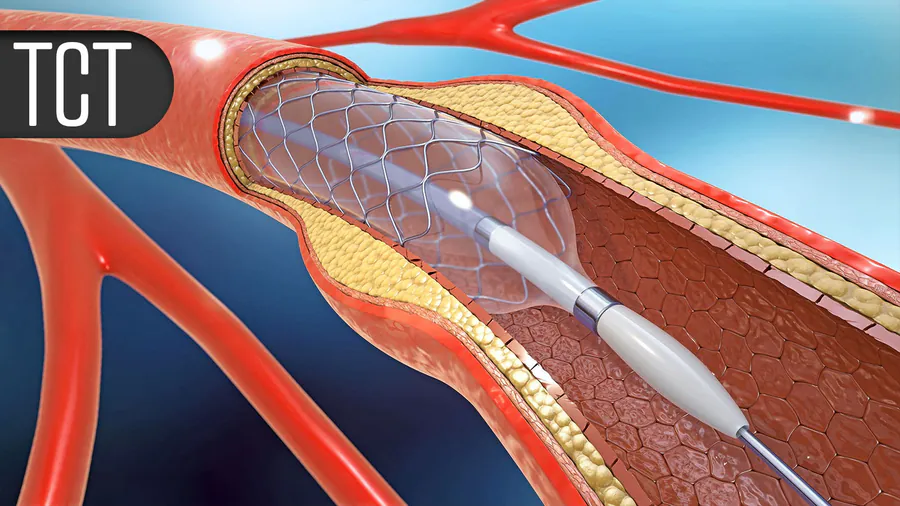
Ditch the double act? The SIMPLAAFY trial found that antithrombotic monotherapy — either aspirin alone or low-dose blood thinners — worked just as well as dual antiplatelet therapy (DAPT) at 6 months after left atrial appendage (LAA) closure. Aspirin emerged as a standout, with fewer bleeds and better tolerability, while low-dose NOACs showed a notably lower rate of device-related clots. The findings could finally bring some clarity to a field long lacking solid guidance.
For patients who've had a left atrial appendage (LAA) closure device implanted, the post-procedure blood-thinning regimen has long been a guessing game. The SIMPLAAFY trial — presented at the Transcatheter Cardiovascular Therapeutics conference and simultaneously published in JAMA — now offers some much-needed answers, showing that simpler antithrombotic strategies work at least as well as the standard dual antiplatelet therapy (DAPT).
The trial randomized 1,857 patients with nonvalvular atrial fibrillation to one of three regimens: aspirin alone, DAPT for 6 months, or reduced-dose NOACs (low-dose apixaban or rivaroxaban) for 3 months. Both monotherapy arms matched or outperformed DAPT on the combined endpoint of death, stroke, systemic embolism, or major bleeding at 6 months. Aspirin was particularly well-tolerated, and low-dose NOACs stood out for a lower rate of device-related clots at 45 days.
By the Numbers:
Why it matters: With no clear standard of care after LAA closure, clinicians have been navigating without solid evidence. SIMPLAAFY provides meaningful data to support simplifying post-procedure regimens — potentially reducing bleeding risk and improving patient adherence — though 12-month data are still pending and some questions around NOACs remain open.