

Turn on cookies to sign in
Signing in saves your progress to your Curie account. We can only do that with cookies on — turn them on to continue.
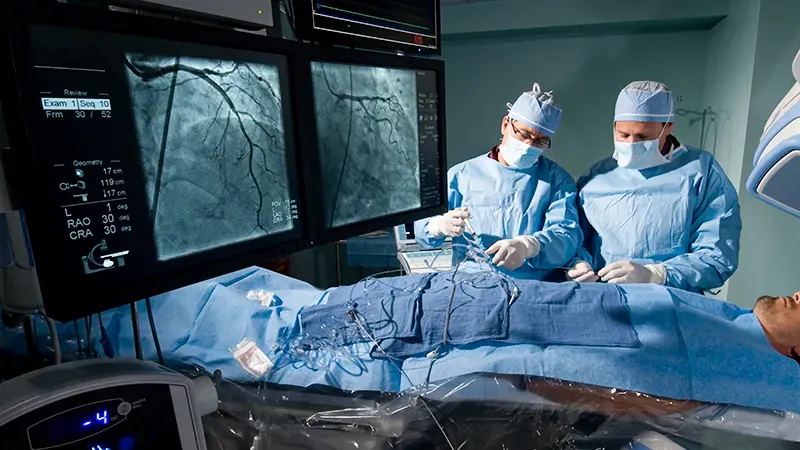
In acute coronary syndrome care, the number of coronary vessels treated during PCI varies dramatically depending on the operator — far beyond what patient characteristics alone can explain. A large Canadian study found the actual range of vessels treated was over 6 times wider than expected. The treating hospital and potentially fee-for-service payment structures may be key drivers of this variation.
A new study published in Heart reveals a striking inconsistency in how aggressively cardiologists treat coronary artery disease during percutaneous coronary intervention (PCI) for acute coronary syndrome (ACS). Analyzing over 72,000 catheterization encounters in British Columbia, Canada, researchers found that the average number of vessels treated per case ranged from 0.455 to 3.19 across 25 operators — a spread more than six times wider than what patient clinical and angiographic profiles would predict.
Notably, operators maintained consistent treatment patterns regardless of whether patients had STEMI or non-ST-elevation ACS, suggesting these tendencies reflect individual practice styles rather than case-by-case clinical judgment. The treating hospital accounted for nearly half (45.6%) of the variation between operators, while operator case volume had no significant effect.
Key Takeaways:
Why it matters: When the same diagnosis leads to vastly different treatment intensity depending on who holds the catheter, it raises important questions about care standardization, patient equity, and whether financial incentives may be quietly shaping clinical decisions.


