Curie Brief
Turn on cookies to sign in
Signing in saves your progress to your Curie account. We can only do that with cookies on — turn them on to continue.
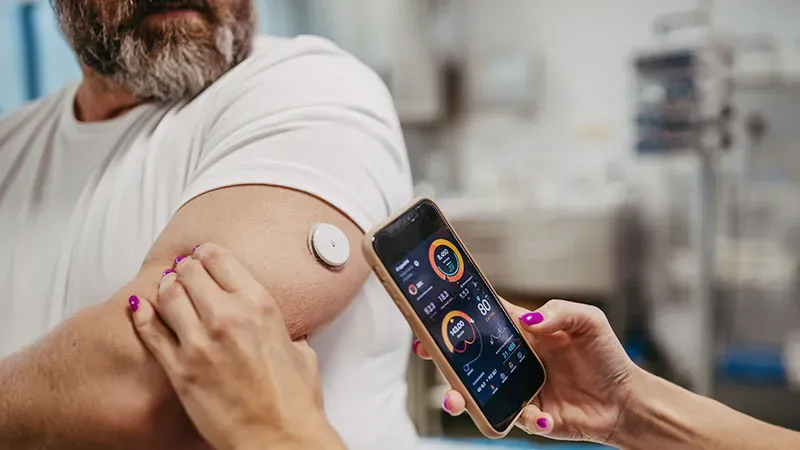
A new study finds that type 1 diabetes patients whose lab A1c reads higher than their continuous glucose monitor estimate face nearly double the risk of microvascular complications. Researchers suggest this "fast glycator" gap could be a valuable risk-stratification tool. Clinicians may want to routinely compare both measures to personalize care and ramp up complication screening.
For people with type 1 diabetes (T1D), the standard A1c blood test and the glucose management indicator (GMI) — an A1c estimate derived from continuous glucose monitoring (CGM) — don't always agree. A new Spanish study of 1,315 T1D patients found that when lab A1c runs higher than the CGM-based GMI, patients face significantly greater risks of eye, kidney, and nerve damage.
The culprit? A phenomenon called "fast glycation" — where sugar attaches to hemoglobin more quickly in some individuals, inflating their lab A1c relative to what their sensor data suggests. About 16% of study participants fit this "fast glycator" profile, and they had nearly twice the odds of microvascular complications compared to others with the same sensor glucose levels.
By the Numbers:
Why it matters: Comparing lab A1c with CGM-derived GMI in routine diabetes care could help clinicians identify high-risk patients earlier, set individualized treatment goals, and increase the frequency of complication screening — potentially preventing serious long-term damage.