


Curie Brief
Turn on cookies to sign in
Signing in saves your progress to your Curie account. We can only do that with cookies on — turn them on to continue.
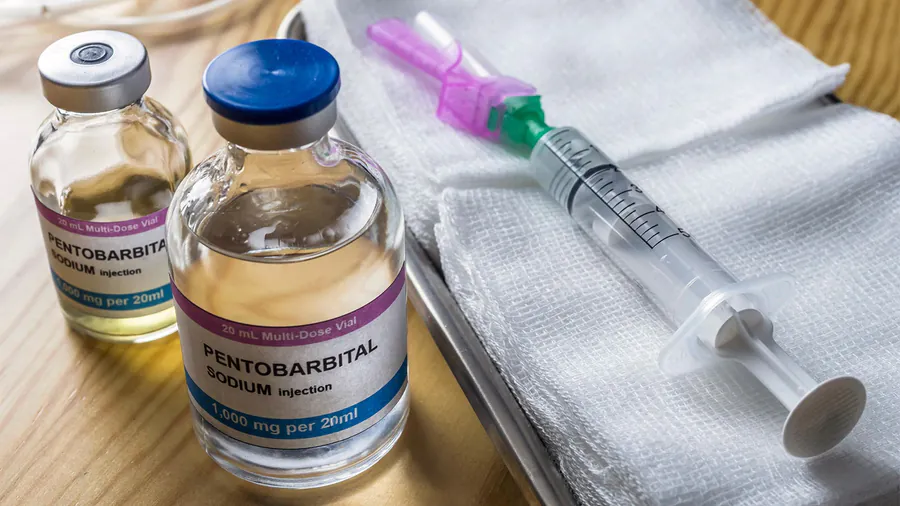
When Christa Pike survived lethal injection in Tennessee, many called it unprecedented. Physicians say it wasn't. A likely IV infiltration — one of the most common complications in clinical medicine — may have prevented the drug from reaching her bloodstream. The real story isn't about a miracle; it's about what happens when the appearance of medicine replaces its actual practice.
When Tennessee executed Christa Pike on September 30 with two doses of pentobarbital and she survived, her lawyers called it "medically unprecedented." Physicians who reviewed the case disagree — and say that's exactly the problem. Burns and blisters on Pike's arms point to IV infiltration or extravasation, a condition where the drug leaks into surrounding tissue instead of entering the bloodstream. It's one of the most common complications of peripheral IV placement, caught routinely by nurses in hospitals many times per shift.
Experts note that Pike's survival wasn't miraculous either — pentobarbital coma is deliberately induced in ICUs to manage seizures and brain swelling, and patients survive with ventilator and blood pressure support, which is precisely what Pike received after being transported to a hospital. The real failure, physicians argue, is that the execution chamber had no mechanism to detect or respond to the IV failure as it happened. Tennessee's protocol allowed no intervention once doses were given — a standard that would shut down any hospital.
Key Takeaways:
Why it matters: This case forces a reckoning with the ethics and mechanics of lethal injection. When the tools of medicine are used without medicine's safeguards — monitoring, trained response, and the freedom to stop — ordinary failures become catastrophic ones. Tennessee's review, physicians say, should ask not what went uniquely wrong, but what could ever have gone right.


