Curie Brief
Turn on cookies to sign in
Signing in saves your progress to your Curie account. We can only do that with cookies on — turn them on to continue.
Mast cell activation syndrome (MCAS) is sparking a heated debate among experts over how — and whether — to diagnose it. Two competing diagnostic frameworks disagree on how much lab evidence is required, leaving many patients in diagnostic limbo. Meanwhile, misinformation online and limited specialist access are making the situation even harder to navigate.
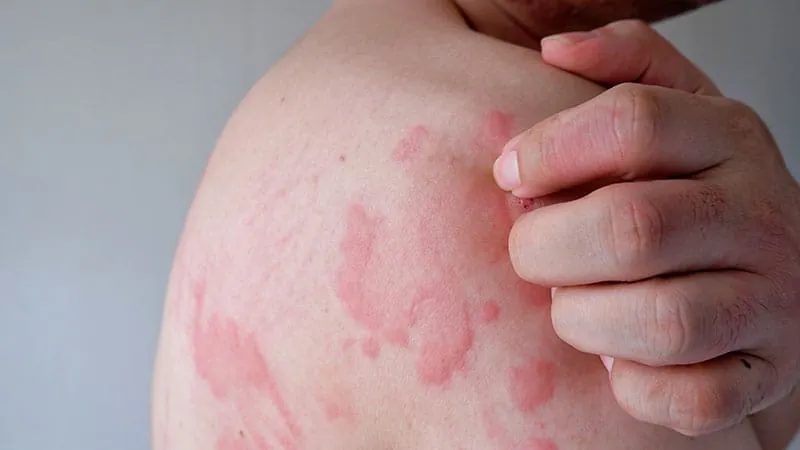
Mast cell activation syndrome (MCAS) — a condition marked by wide-ranging symptoms like hives, flushing, anaphylaxis, and GI distress — is drawing growing attention from patients and clinicians alike. But a fundamental disagreement over how to diagnose it is leaving many patients without answers, sometimes for a decade or more.
At the heart of the dispute are two competing diagnostic frameworks. The narrower "consensus 1," endorsed by the American Academy of Allergy, Asthma & Immunology, requires objective lab evidence of elevated mast cell mediators (notably serum tryptase) alongside recurrent multisystem symptoms and response to treatment. The broader "consensus 2" accepts a wider range of symptoms and lab findings and doesn't mandate an abnormal mediator test — leading its proponents to estimate MCAS may affect up to 17% of the population, a figure consensus 1 supporters strongly dispute.
Experts on both sides agree that patients are suffering, but diverge on the risks of over- vs. underdiagnosis — and on whether current testing tools are adequate to capture the full complexity of mast cell activity.
Key Takeaways:
Why it matters: With specialist referrals rising and misinformation spreading on social media, clinicians face pressure to balance diagnostic rigor with compassion — ensuring patients aren't dismissed, but also aren't misdiagnosed in ways that delay finding the real cause of their symptoms.