Curie Brief
Turn on cookies to sign in
Signing in saves your progress to your Curie account. We can only do that with cookies on — turn them on to continue.

Hormone replacement therapy (HRT) for menopause should be tailored to each woman's symptoms, risks, and preferences — not applied as a blanket solution. Experts at the Royal College of Physicians of Edinburgh stressed that lifestyle changes come first, perimenopause can't be confirmed by a single hormone test, and transdermal oestrogen carries a lower thrombosis risk than oral forms. The bottom line: individualized, evidence-based care is key.
Menopause management got a nuanced update at the Royal College of Physicians of Edinburgh's "Modern Medicine: Menopause" lecture, where specialists Claire Phipps and Sarah Glynne made one thing clear: there's no universal playbook for HRT. With at least 75% of women experiencing menopausal symptoms and about 25% seeking medical help, the experts emphasized that care is still falling short — some symptoms are dismissed, others are over-attributed to menopause without proper evaluation.
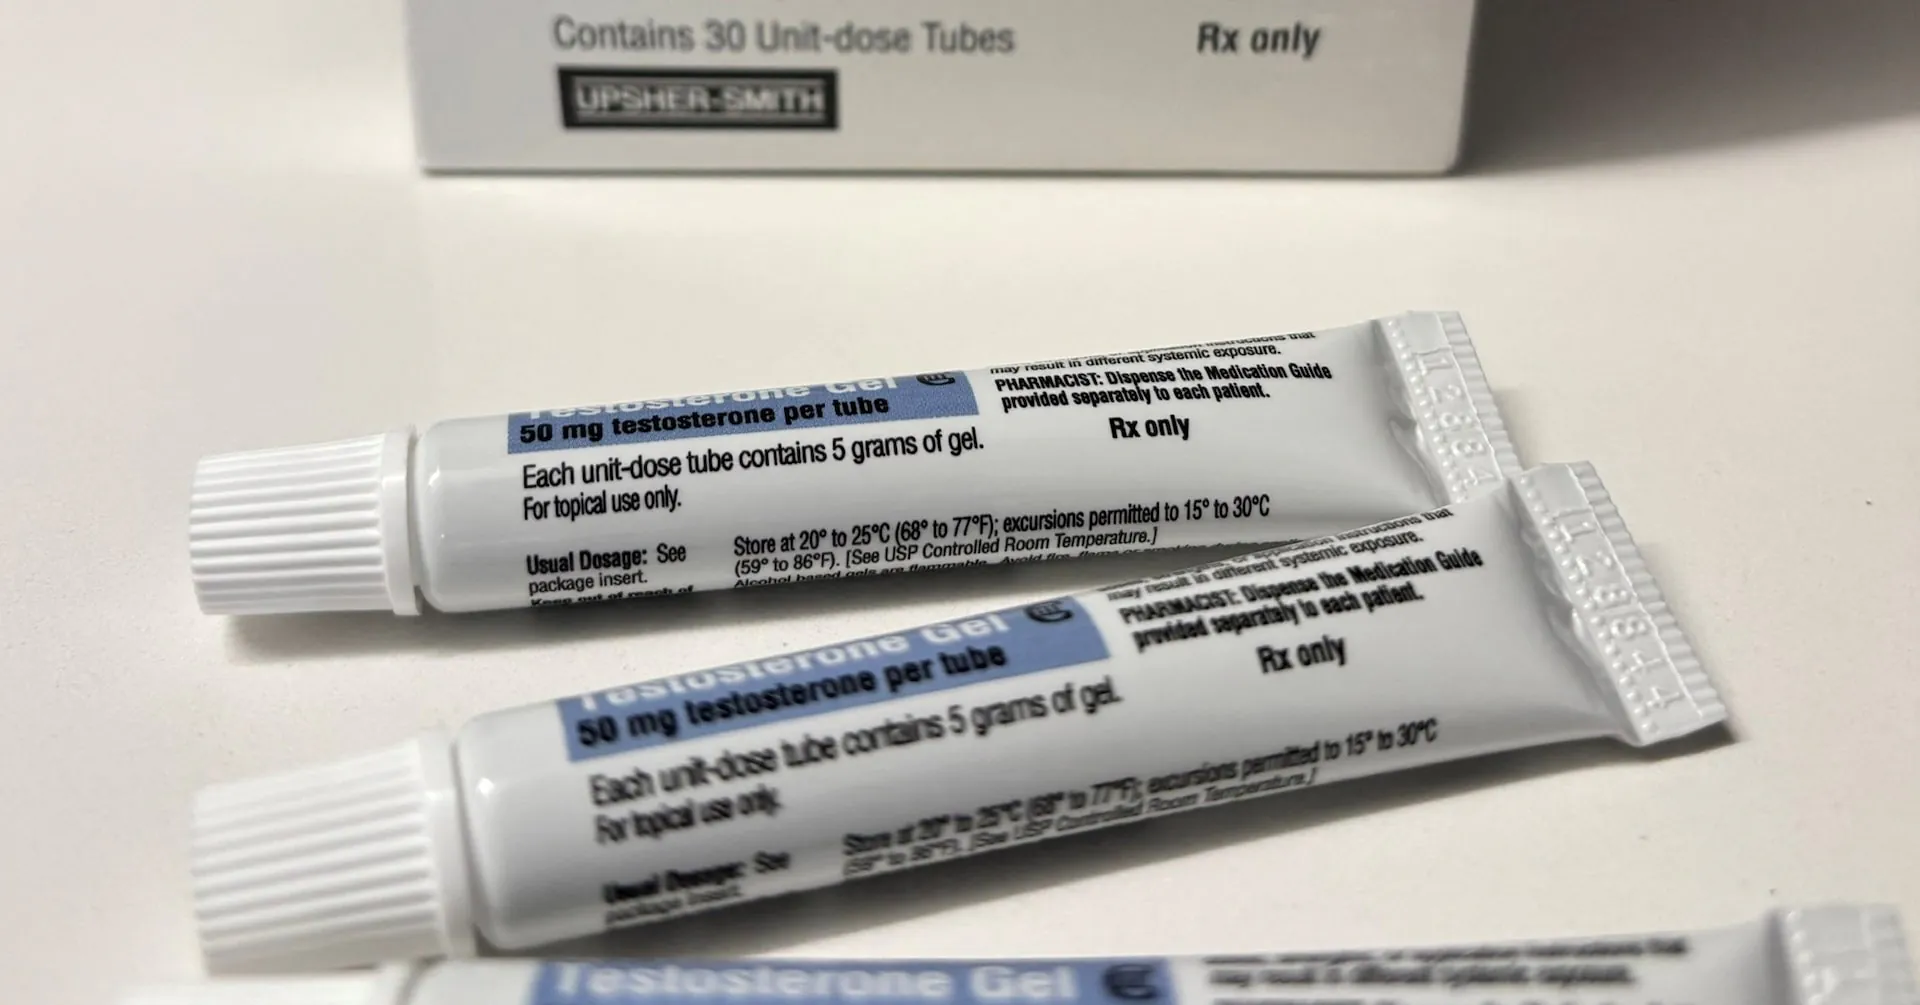
The recommended approach starts with lifestyle: regular physical activity (including strength training and yoga), a calcium-rich diet, good sleep hygiene, and cutting back on alcohol and spicy foods. When medication is needed, HRT remains the most effective option for hormone-deficiency symptoms, but the route matters — transdermal oestrogen (patches, gels, sprays) does not raise thrombosis risk the way oral oestrogen does. Non-hormonal options like venlafaxine and menopause-specific cognitive behavioural therapy can also play a role.
Key Takeaways:
Why it matters: With millions of women navigating menopause, clinicians need individualized, evidence-based frameworks — not blanket rules — to provide effective, safe, and compassionate care.